Department
Radiology & Imaging
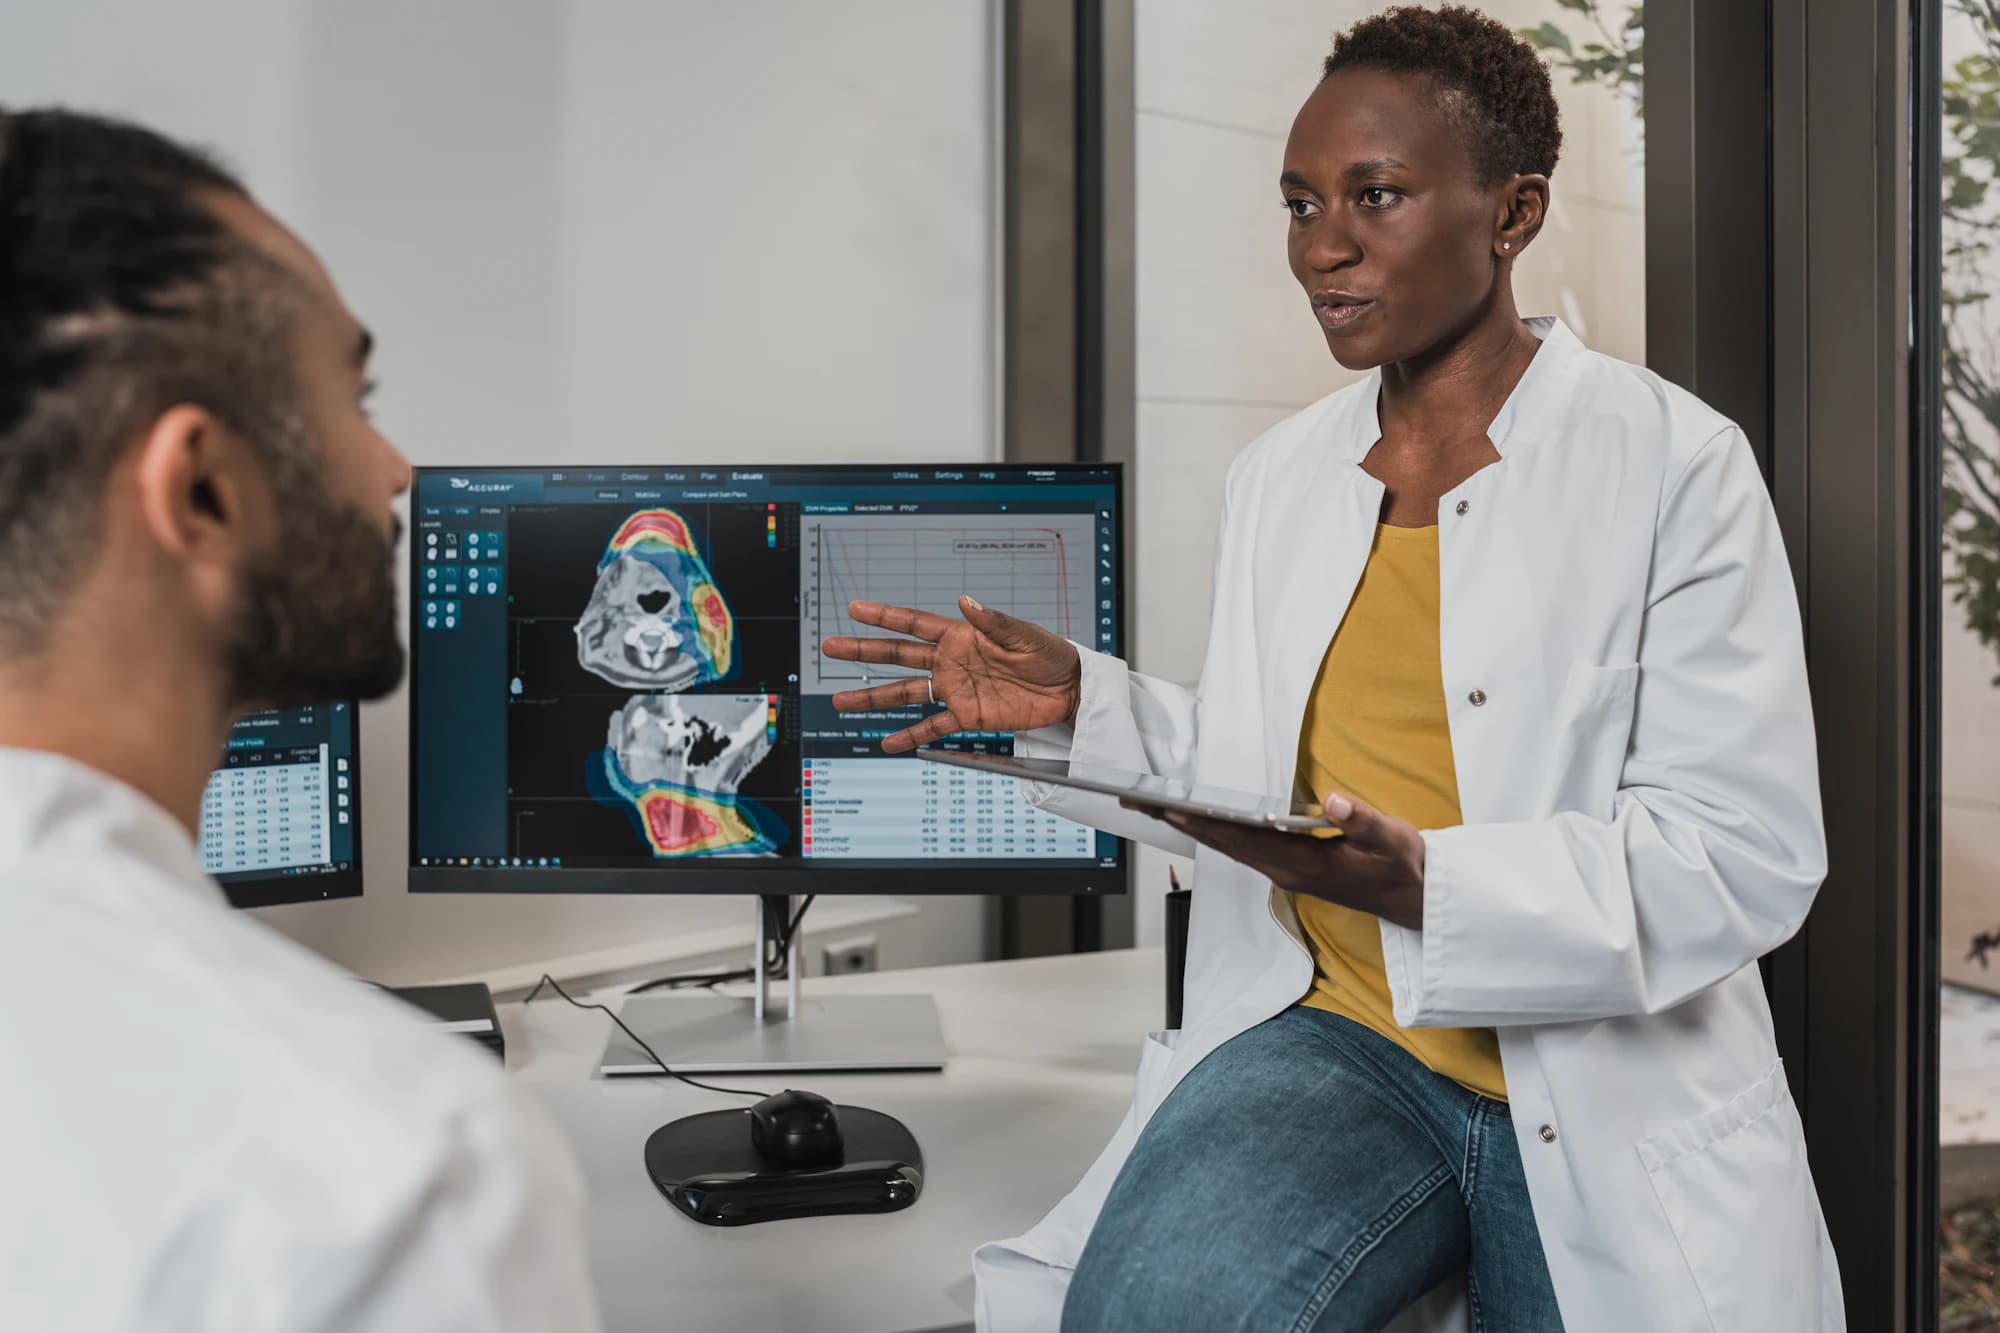
Radiology is the department where the work is digital from end to end and the coordination is still done on paper. The modality worklist is typed by hand, the study lands in an archive the record cannot see, and the report is carried back as a printout.
The digital department that runs on paper.
Every object in radiology is already a file. The reason a scan takes a day to reach a clinician is that the file and the request were never the same object.
A patient is registered at the imaging counter a second time. A technologist types the name into the modality because the worklist is empty. The study lands in an archive with a slightly different spelling. The report is dictated, typed, printed and carried. Each of those steps is a place where a study and a patient can come apart.
India adds a scarcity multiplier to all of it. Reporting capacity is the constraint, which is why so much of it is bought from outside the hospital.
Impact and action
The worklist is typed at the console.
- The technologist keys the patient into the modality by hand, so the study carries whatever was typed rather than the hospital's identity for that person.Forge turns the order into a modality worklist entry over DICOM MWL, so the machine is loaded with the hospital's own identity and the study can only attach to the order that created it.Forge
- A study lands in an archive the clinical record has no view of, and the clinician goes to the department to look at it.The orophin bridge carries the completed study back, and Atlas opens it in the viewer next to the note that ordered it, with zoom, pan and measurement.AtlasWestron
The report and the finding are two different journeys.
- A significant unexpected finding is written into a report that reaches the referring clinician days later, or reaches a clinician who has already gone off service.Sentinel raises the critical finding as an owned alert with an escalation chain, separately from the report itself, and records whether it was acknowledged.SentinelRaven
- Reporting turnaround is argued about rather than measured, and the backlog is discovered when a clinician complains.Falcon reports turnaround by modality, by reporting radiologist and by referring department, off the order record itself.Falcon
The scan is charged after the fact.
- Contrast, films, sedation and repeat sequences are noted on a slip and added to the bill by somebody reading it later.Each of them is captured at the point of use as an order, and Vault adds the charge in the same movement, at the price the catalogue held that day.ForgeVault
- A cashless authorisation stalls because the study report has to be found and attached by hand.The report is already attached to the visit the claim is built from, so the pack is assembled rather than collected.Vault
The study
Request to report.
The order
A clinician orders the study with its indication and priority. The order carries the patient, the visit and the clinical question the radiologist will be answering.
Scheduling
The slot is booked against the modality as a real resource, with preparation instructions issued to the ward or sent to the patient before the appointment.
Acquisition
The order appears on the modality worklist over DICOM MWL. The technologist selects rather than types, and the study is bound to the order from the first image.
Reporting
The study is read in the viewer, and the report is a structured, locked document tied to the same order, whether it is read inside the hospital or outside it.
Return
The report lands on the record it was ordered from. A critical finding is an alert with an owner, and the charge is already on the bill.
The tools this department lives in.
Read top to bottom. Each tag is a tool inside Pensieve, and the line beside it is what that tool does in an imaging department specifically.
| Tool | What it does in this department |
|---|---|
| Forge | The imaging order, its DICOM worklist entry, contrast and consumable capture, and its route to an outside reporter. |
| Westron | The connections to modalities, the archive and any teleradiology service, with translation and a forensic trail. |
| Atlas | The record the study returns to, and the in-app viewer with zoom, pan and measurement beside the ordering note. |
| Gate | Slot scheduling against each modality as a resource, and the patient's movement to and from the department. |
| Glyph | Contrast consent, safety screening questionnaires, and the structured report itself, locked on completion. |
| Sentinel | The critical or unexpected finding as an owned alert with an escalation chain, separate from the report. |
| Vault | The charge for the study, the contrast and the films, at the price the catalogue held on the day of the scan. |
| Falcon | Turnaround by modality and by reporter, repeat rate, utilisation by hour, and outsourced reporting spend. |
| Vigil | Equipment maintenance evidence, radiation safety records and the department's accreditation file. |
Published research
What the literature already measured.
Findings about imaging work, each with its study and a link. None of it is a Pensieve result.
- A review of radiological error puts the day to day discrepancy rate between reporting radiologists at 3 to 5 percent, and treats failure to communicate a finding as its own category of harm.Brady AP. Insights into Imaging, 2017. Communication failure is counted separately from misreading.
- A National Academies review concluded that most people will experience at least one diagnostic error in their lifetime, and named information that fails to reach the decision as a recurring contributor.National Academies of Sciences, Engineering, and Medicine. Improving Diagnosis in Health Care, 2015.
- Across four specialties, physicians spent 49.2 percent of the office day on the record and desk work, and 27.0 percent in direct time with patients.Sinsky C, Colligan L, Li L, et al. Annals of Internal Medicine, 2016. Chasing a report is part of that half.
Radiation safety
The register that belongs to the machine.
Radiation equipment sits under the atomic energy regulator, and the obligation attaches to the machine rather than to the study.
- Equipment approval, service history and personnel monitoring are kept per machine, and Vigil holds them as live evidence rather than as a folder assembled for an inspection.
- Quality assurance tests and their due dates run as schedules against the same asset the maintenance team works from, so one plan covers the clinical requirement and the statutory one.
- Consent for contrast and for an interventional procedure is a signed artefact with a formal sign-off, attached to the study it belongs to.
Delete the trip to the department. A study, the request that produced it and the report that answers it should be one object, and a clinician should meet all three in the record.
Governance and statute
The reading room carries a criminal liability.
Every prenatal diagnostic procedure performed in India requires a completed statutory form, retained and submitted with the report, the images and the referring clinician’s own sheet. The liability attached to getting it wrong is criminal rather than civil, and it attaches to the radiologist personally. No imported product contains this form, which is why it is the first thing an Indian radiology department asks about.
The form is built by the hospital, and it locks.
Glyph builds the statutory forms the department is answerable for, with the validations and the calculators the department wrote, and with no developer in the loop. A completed form locks the moment it is finished, so it can never be silently altered afterwards, and Glyph keeps the version history that proves which design was in force when it was filled. A form hangs directly off the order it belongs to.
The study and the note it was ordered from share a record.
Discrepancy between readers is a normal working rate rather than an anomaly, and the failure that does damage is a finding that never reaches the person acting on it. Source 13 The imaging viewer opens a study against the right patient and the right order from wherever the reader is in the app, and a critical finding becomes an owned alert with an escalation chain rather than a line in a report nobody opened.
Reading from outside the hospital is a governed path.
India has roughly one radiologist for every hundred thousand people, so studies are read remotely as a matter of routine. Cirith decides per action whether a specific reader may open a specific study, an administrator can look up everything one reader can reach, and every access is logged.
Interoperability and federation
Where the images actually live.
- The archive you already own.The bridge connects the modality and the archive the hospital already runs. Pensieve replaces the coordination problem across systems rather than the hardware, and export speaks DICOM so the studies stay portable.
- Teleradiology across sites.A group reads across units. One worklist, one identity, one governed access model, with each unit keeping its own statutory register and its own accreditation file.
- Contrast, film and consumables.Pensieve integrates with the inventory system a hospital already runs. Where there is none, the app is built in [Durin](/tools/durin), either by hospital staff with no code and no vendor ticket, or by a Pensieve forward-deployed engineer who builds it for the hospital and hands it over. Anything built that way sits on the same permissions and the same audit trail as the rest of the platform.